
5 key points about negative blood culture and fever
Learn what blood metagenomic analysis may add when fever persists despite a negative culture, and how to interpret its limits alongside clinical assessment.
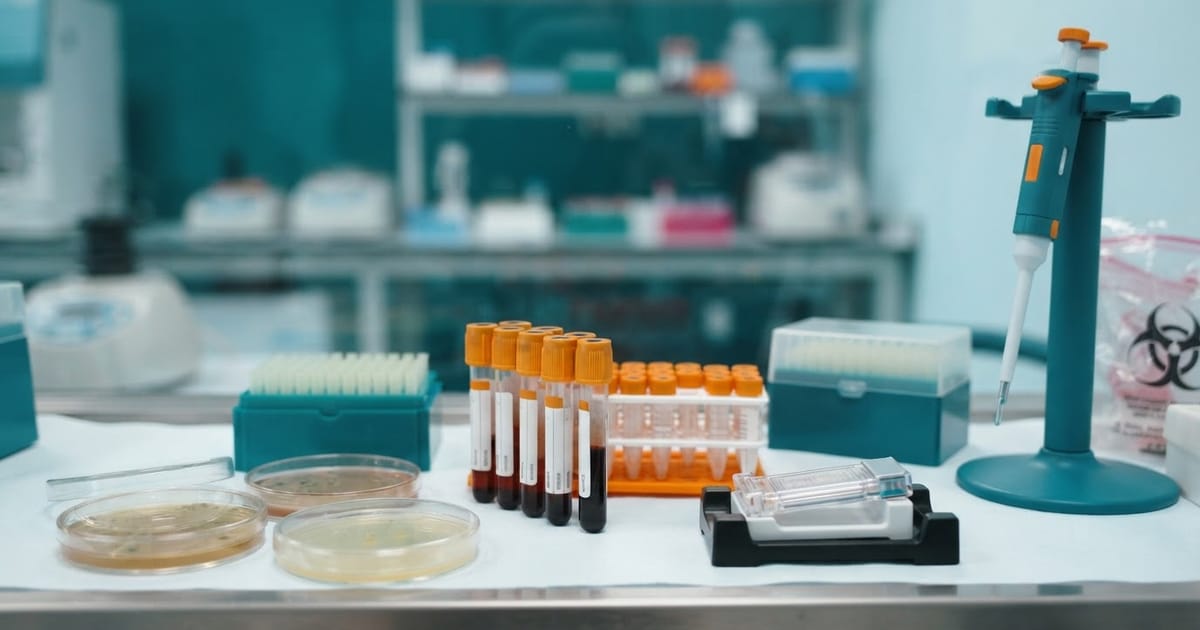
When blood culture is negative but fever persists, metagenomic analysis of blood may provide complementary information about microbial genetic material. It does not replace clinical assessment, conventional cultures or other diagnostic tests.
In summary:
- A negative blood culture does not, on its own, establish the cause of persistent fever or rule out all infections.
- Metagenomic analysis of blood examines genetic material present in the sample and may complement culture and clinical assessment when infection is suspected.
- The result should be interpreted alongside the clinical history, physical examination, previous medication, sample quality and other available tests.
- Metagenomic sequencing does not replace urgent assessment of an unstable patient, nor does it allow treatments to be started, modified or discontinued without medical judgement.
The usefulness of a clinical metagenomic analysis of infections in blood depends on each patient’s context and on correlation with the other clinical and microbiological findings.
What can metagenomic analysis contribute when the blood culture is negative?
Metagenomic analysis of blood can look for microbial genetic material in a clinical sample and provide an additional line of investigation when blood culture does not identify an agent. Its usefulness depends on the clinical suspicion, sample quality, microbial load and professional interpretation of the result.
Unlike culture, which attempts to recover viable microorganisms under specific conditions, metagenomic sequencing analyses the genetic material present in the sample. It can therefore complement cultures and other tests, but it does not by itself demonstrate that a finding is the cause of the fever.
Before requesting it, it is advisable to review:
- symptoms, examination findings and clinical progression;
- previous antibiotics or other treatments;
- culture, imaging and specific test results;
- the type, quality and timing of sample collection.
The information provided by metagenomic analysis of blood should be integrated with the clinical and microbiological assessment. An isolated result should not be used to start, change or discontinue treatment without medical judgement.
Why can a blood culture be negative if fever persists?
A blood culture may be negative even if fever persists because of antibiotics given before the sample was collected, a low number of microorganisms in the bloodstream, problems with sample collection or processing, organisms that are difficult to grow in culture, or a non-infectious cause; the clinical context determines which possibility is more likely.
For this reason, the result should be reviewed alongside:
- the timing of sample collection and previous medication;
- the volume and quality of the sample;
- the conditions for transport, incubation and processing;
- the possibility of microorganisms that do not grow easily in culture;
- other causes of fever, such as inflammatory processes or medication.
A negative result alone does not confirm an infection with a negative blood culture or rule it out. If a serious infection is suspected, the healthcare professional may consider additional tests, such as an analysis for urgent infections, always interpreting them together with the physical examination, the clinical course and the rest of the results.
In which patients can a metagenomic blood test be considered?
The test may be considered, at the clinician’s discretion, when there is a reasonable suspicion of infection despite inconclusive or conflicting conventional results, especially if fever persists, the clinical situation is concerning, or previous medical history and treatments make it difficult to interpret the initial tests; it is not a screening test for every febrile episode.
It may be considered in patients with:
- Persistent fever without a clear clinical explanation.
- Suspected severe infection or an unfavourable clinical course.
- Discrepancies between symptoms, examination findings and microbiological results.
- A need to extend the investigation after reviewing the available samples and tests.
The decision should take into account the patient’s stability, the prior probability of infection, the antimicrobials received and the clinical question the test is intended to answer. It should not delay urgent care or lead to changes in treatment without medical judgement. Healthcare professionals can consult the professionals’ access to review the ordering process and the clinical information required.
How is a positive or negative metagenomic result interpreted?
A positive metagenomic result means that genetic material consistent with a microorganism has been detected, but it does not by itself demonstrate an active infection; a negative result does not rule out all infections either. Both findings must be assessed alongside symptoms, physical examination, cultures, imaging, treatments and the clinical course.
The detection may reflect:
- active infection;
- genetic material from non-viable microorganisms;
- sample contamination;
- colonisation or the presence of a microorganism unrelated to the fever.
For this reason, clinical relevance depends on the consistency between the microorganism detected, the suspected source and the rest of the test results. An isolated or unexpected finding may require confirmation using another method or a new sample. Likewise, a negative result may be due to an insufficient quantity of microbial material, the type of sample or an organism not covered by the analytical scope of the test.
The interpretation should be carried out by the responsible healthcare team, with support from tools such as Sophia, clinical AI, without starting, changing or stopping treatment based solely on the report.
What are the limitations of metagenomic analysis in blood?
Metagenomic analysis in blood has technical and clinical limitations: a low amount of microbial material can reduce detection, while contamination or genetic material from non-viable microorganisms can make it difficult to establish causality and may require confirmation using other methods.
Sensitivity can vary depending on the sample, the microorganism and the method used. For this reason, a negative result does not rule out all infections, and a positive result should be assessed alongside the clinical presentation, culture results and the patient’s progress.
Metagenomic sequencing is not necessarily equivalent to a complete antimicrobial susceptibility test: detecting genetic material does not guarantee that there is enough information about antimicrobial susceptibility to determine treatment. Relevant findings should be confirmed, and the stated scope of each test in the Xenogene analysis catalogue should be reviewed.
Frequently asked questions
What information should the doctor provide when requesting a metagenomic analysis?
The doctor should provide the clinical and microbiological information needed to interpret the result: reason for the request, fever progression, suspected infection, previous antimicrobial treatments, samples analysed and available results. This information helps assess whether the genetic material detected is clinically relevant and integrate it with the examination and other tests.
Can a metagenomic result confirm the source of the infection on its own?
No. Detecting microbial genetic material may provide a clue, but it does not, on its own, identify the source of the infection or necessarily demonstrate causality. The finding must be interpreted in relation to the symptoms, examination, imaging tests, cultures, other clinical samples and the patient’s progress.
Can the test indicate which antimicrobial treatment should be used?
Not necessarily. A metagenomic analysis can provide information about the microorganisms detected, but the treatment decision depends on the clinical picture, the likely source, the severity of the condition, microbiological results and the available information on antimicrobial susceptibility. Treatment should not be started, changed or stopped based solely on this result.
What does it mean if the result does not match the culture results?
A discrepancy between the metagenomic analysis and the cultures requires professional review, not an automatic conclusion. It may be related to differences between detecting genetic material and recovering viable microorganisms, contamination, the amount of microorganism present or the characteristics of each sample. The result must be considered alongside the clinical context and the other test findings.
When does a person with persistent fever require urgent medical attention?
Persistent fever requires medical assessment, and urgent care should be sought if it is accompanied by marked deterioration, confusion, difficulty breathing, fainting or other signs of severe illness. A metagenomic test must not delay medical attention or replace the immediate assessment of an unstable person. The healthcare professional will decide which tests and measures are needed.
Request information about clinical metagenomic analysis of infections in blood
Sources
Other related tests
- VERUM
Cancer Liquid biopsy for Early Analysis and Response
- Microbiota Esencial
Análisis metagenómico clínico dirigido a la evaluación cuantitativa y cualitativa de los 150 microorganismos intestinales más relevantes para la salud humana.